


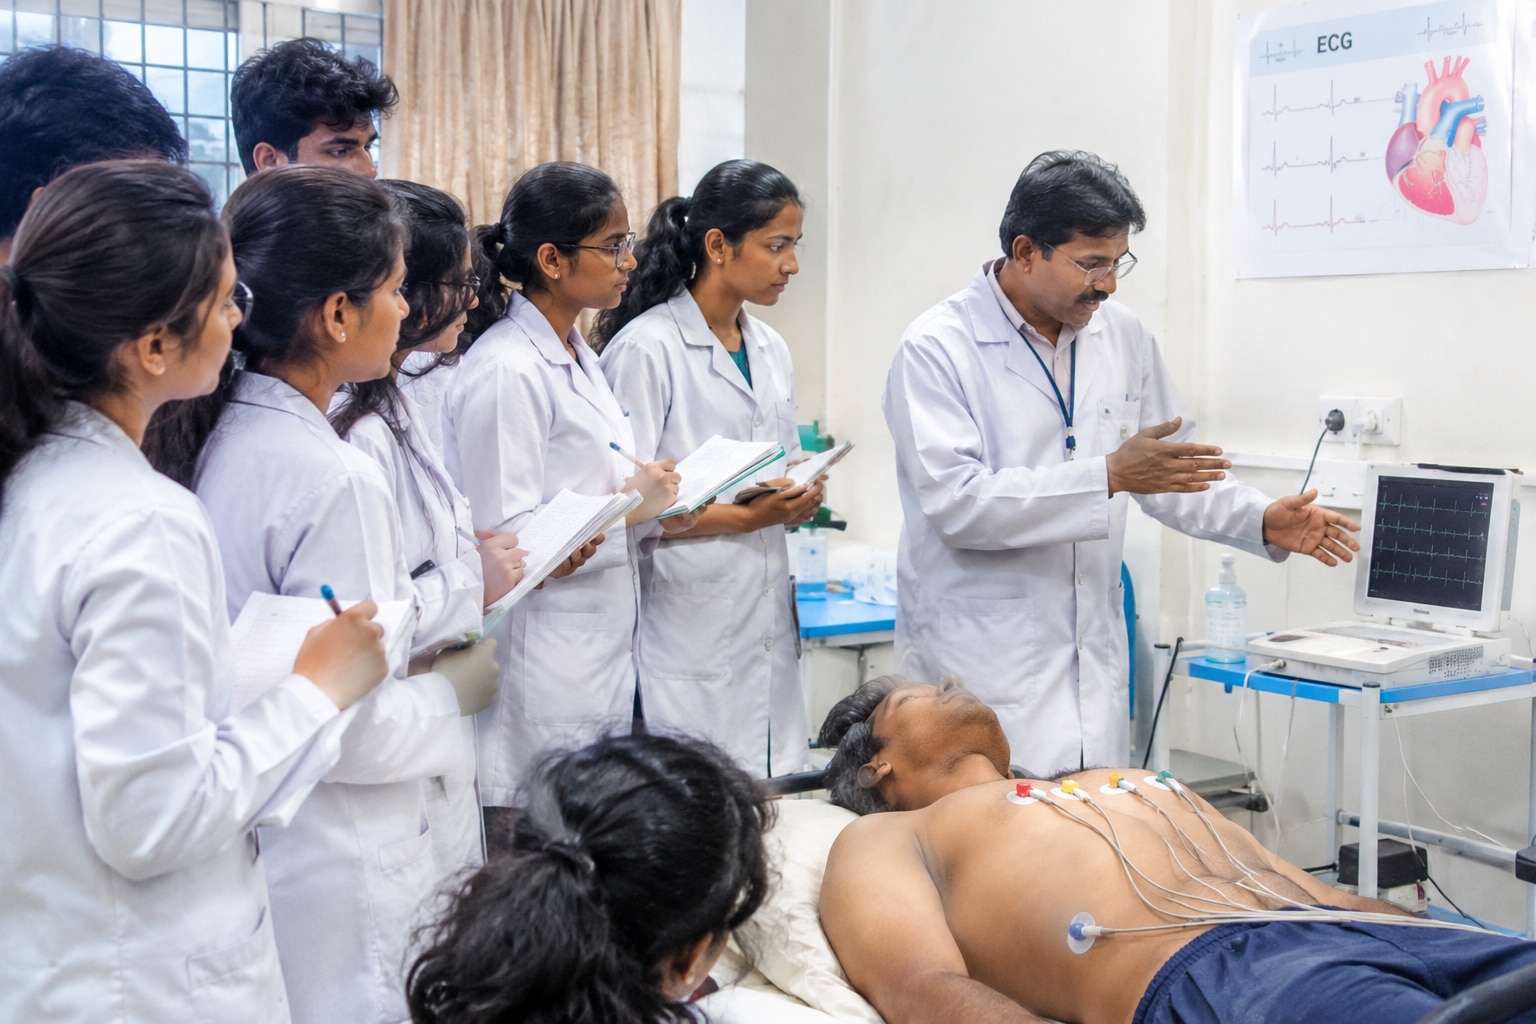
An ECG course is valuable only when it teaches you to produce an accurate tracing, identify technical faults and understand where technical recording ends and clinical diagnosis begins. By the end, you should know what to practise, what equipment settings and lead positions matter, and how to judge whether a nearby course prepares you for supervised clinical work.
Key takeaways
- Place the four limb and six chest electrodes correctly before recording.
- Reject tracings with baseline wander, muscle tremor, or loose-electrode artefact.
- Compare courses by supervised practice, equipment access, and assessment method.
- An ECG shows electrical activity, not blood flow or heart muscle movement.
What an ECG records—and how each test differs
An ECG records the electrical activity of the heart—not blood flow or heart muscle movement. It shows rate (beats per minute), rhythm (regularity and electrical origin), conduction intervals (timed electrical travel through the atria, AV node and ventricles), and waveform changes in P waves, QRS complexes, ST segments and T waves.
A standard diagnostic 12-lead ECG uses 10 electrodes:
- Four limb electrodes generate leads I, II, III, aVR, aVL and aVF.
- Six chest electrodes generate leads V1–V6.
| Test | What it records | Main use |
|---|---|---|
| Resting 12-lead ECG | A brief, multi-angle tracing at rest | Assess rhythm, conduction, axis and waveform abnormalities |
| Rhythm strip | One or a few leads over a short period | Follow rate and rhythm, especially during an episode |
| Holter monitoring | Ambulatory ECG over roughly 24–48 hours or longer | Capture intermittent symptoms or paroxysmal arrhythmias |
| Exercise stress testing | ECG during increasing physical workload | Assess exercise-related electrical changes and symptoms |
| Telemetry | Continuous remote monitoring in a clinical setting | Detect changing rhythm or rate during care |
Rhythm-strip practice alone is not 12-lead training: it does not teach chest-lead positioning or multi-lead diagnostic comparison. A printed ECG is a snapshot, not a complete assessment of cardiac health. A normal tracing does not exclude acute coronary syndrome, and automated comments require clinician review alongside symptoms, examination and other tests.
The hands-on sequence for acquiring a 12-lead ECG
A reliable 12-lead ECG begins before the machine records. Confirm patient identification using the name and a second identifier, explain the brief electrical recording, and provide privacy. Position the patient supine when tolerated; document if symptoms require another position.
1. Perform skin preparation: expose the required areas, clean away oil or sweat, dry the skin fully, and clip hair that prevents contact. Do not place electrodes over clothing, wounds, or heavy lotion.
- V1: fourth intercostal space at the right sternal border
- V2: fourth intercostal space at the left sternal border
- V4: fifth intercostal space on the mid-clavicular line
- V3: midway between V2 and V4
- V5: horizontally level with V4 at the anterior axillary line
- V6: horizontally level with V4 at the midaxillary line
3. Apply each electrode firmly, then perform lead connection and check that every cable label matches its electrode. A misplaced V1 or V2 can create a false anterior pattern.
4. Confirm the standard settings: paper speed 25 mm/second and gain 10 mm/mV. A faster speed can spread out a very fast rhythm; increased or reduced gain can display prolonged intervals or large voltage, but retain the standard setting context and calibration mark.
5. Ask the patient to remain still, relax the limbs, and avoid talking. Record, inspect, and safely remove electrodes while supporting the skin.
How to detect artefact and reject a poor tracing
Reject a tracing before interpreting it. Loose or dry electrodes cause intermittent signal and abrupt baseline shifts; skeletal-muscle tremor produces irregular, high-frequency interference; and nearby electrical equipment can create 50/60-Hz electrical interference. Baseline wander often follows breathing, movement or poor skin contact. These patterns can mimic arrhythmia or ST-segment disease.
- Inspect the patient. Ask them to relax, keep still, uncross their legs and stop talking. Look for shivering, muscle tension, sweating or movement.
- Inspect every cable and electrode. Press down loose electrodes, replace dry or lifted electrodes, clean and dry the skin, and move electrical equipment away from the ECG.
- Verify placement. V1 belongs at the fourth intercostal space at the right sternal border and V2 at the left sternal border. Misplaced V1–V2 can create a false anterior pattern or suggest right-heart strain.
- Check for reversed limb leads. They can alter the axis and invert expected waveforms. Correct the connection or placement, then repeat the ECG.
Do not label artefact as disease. Release the repeat only after checking the patient name or identifier, date and time, lead labels, paper speed, the 10 mm/mV calibration mark, signal quality and symptoms reported during recording. If the tracing remains noisy or clinically inconsistent, document the problem and obtain help before interpretation.
How to compare an ECG course near you before enrolling
A short certificate is not proof of practical competence. Compare each local 12-lead diagnostic course against the work you will actually perform.
- Check for repeated supervised 12-lead recordings, correct landmarking and repositioning of V1–V6, and timed practice for urgent presentations.
- Ask whether learners troubleshoot artefact, adjust machine settings, complete documentation, and review real or simulated poor-quality tracings.
- Confirm that assessment tests electrode placement, acquisition and quality control, not only memorised waveform names.
- Ask who supervises practical sessions, which ECG machines learners use, and how many recordings each learner completes.
- Ask whether automated ECG statements are taught as an aid requiring clinician review, never as a final diagnosis.
- Request the exact certificate title, issuing body, registration status and duties it supports.
| Course feature | Strong evidence | Warning sign |
|---|---|---|
| Practical assessment | Observed recordings and quality checks | Written quiz on waveform names |
| Equipment | Learners operate clinical ECG machines | Demonstration only |
| Urgent care | Timed practice and escalation communication | No time-based scenarios |
| Poor tracings | Correction and repeat-recording practice | Only perfect examples |
| Credential | Clear scope and registration information | Vague “certified” wording |
Recording and quality-checking an ECG fits a technician role; independently diagnosing myocardial infarction, arrhythmia, ischemia or electrolyte disturbance, or issuing an unsupervised clinical report, requires a qualified clinician, local authorisation and employer protocols. Check supervision and local authorisation requirements before enrolling.
If comparing options in Pune, ask KP PARAMEDICAL INSTITUTE PCMC these questions rather than choosing by location or certificate title alone.
What trained ECG skills can—and cannot—tell you clinically
A normal first ECG does not rule out acute coronary syndrome. Ischaemic changes can evolve, so persistent chest pain, breathlessness, syncope, or ongoing suspicion requires clinical escalation and, when directed, repeat or serial ECGs. For suspected acute coronary syndrome, acquire the tracing as soon as possible, ideally within 10 minutes of first clinical contact.
A trained operator can produce an interpretable tracing and recognise patterns supporting STEMI, arrhythmia, conduction disease, or electrolyte disturbance. The computer-generated interpretation is an aid, not a diagnosis; integrate the tracing with symptoms, examination, prior ECGs, medications, biomarkers, and imaging.
A serious course should frame these advanced limits:
- If a 12-lead ECG misses suspected paroxysmal atrial fibrillation, use clinician-directed ambulatory monitoring; an irregular pulse or wearable alert is not diagnostic confirmation.
- Teach QTc Bazett and Fridericia correction as heart-rate corrections, not interchangeable labels. Bazett overcorrects at fast rates and undercorrects at slow rates.
- Practise timed acquisition, recognition, documentation, and escalation—not just waveform-name recall.
ECG training builds reliable acquisition, recognition, and communication skills. It does not grant independent authority to diagnose every cardiac condition or issue an unsupervised report; follow qualified-clinician oversight, local authorisation, and employer protocols.
Frequently asked questions
What does an ECG record?
An ECG records the heart’s electrical activity, including rate, rhythm, conduction intervals, and P-wave, QRS, ST-segment, and T-wave changes. It does not directly measure blood flow or heart muscle movement.
How do you acquire a 12-lead ECG?
Prepare the patient, place the four limb electrodes and six chest electrodes accurately, check skin contact, record the tracing, and label it with patient details, date, and time.
How can you identify a poor ECG tracing?
Look for baseline wander, muscle tremor, electrical interference, inconsistent lead signals, and loose electrodes. Correct the source and repeat the recording when artefact obscures the waveform.
How should you compare an ECG course near you?
Check whether the course provides supervised 12-lead practice, working ECG machines, instruction on artefact correction, competency assessment, and clear limits on clinical interpretation.
What can trained ECG skills tell you clinically?
They help you acquire and recognise patterns in rate, rhythm, conduction, and waveform changes. They do not replace clinician interpretation, patient assessment, or tests such as echocardiography and cardiac imaging.


